
Long SFA lesions present complex challenges for endovascular management
As lesion length increases in the superficial femoral artery (SFA), treatment outcomes typically worsen, with decreased patency demonstrated in studies of drug-eluting stents, drug-coated balloons, and bare metal stents.1-4
Proven outcomes in long SFA lesions
The GORE® VIABAHN® Endoprosthesis with Heparin Bioactive Surfacea,b has demonstrated excellent patency and durability independent of lesion length.4-7
See the latest data

The Gore Japan Post-Market Clinical Study
A prospective, multicenter (64 sites), 5-year follow-up building on 1-year post-market surveillance.6,7
- 324 lesions, 24 cm average lesion length
- 70% chronic total occlusions (CTO)
- 27% critical limb-threatening ischemia (CLTI)
- 48% TASC II D lesions
PROVEN PATENCY
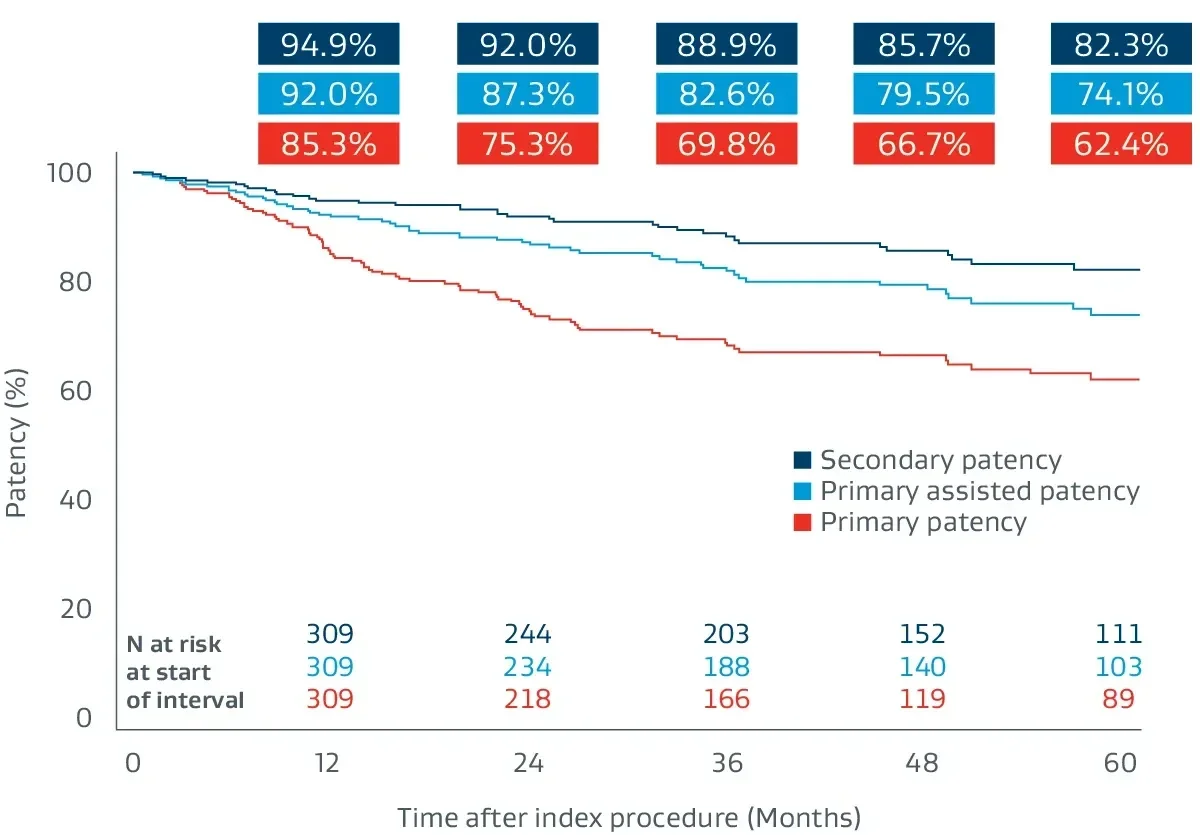
Patency through 5 years in challenging SFA disease7
DEMONSTRATED DURABILITY
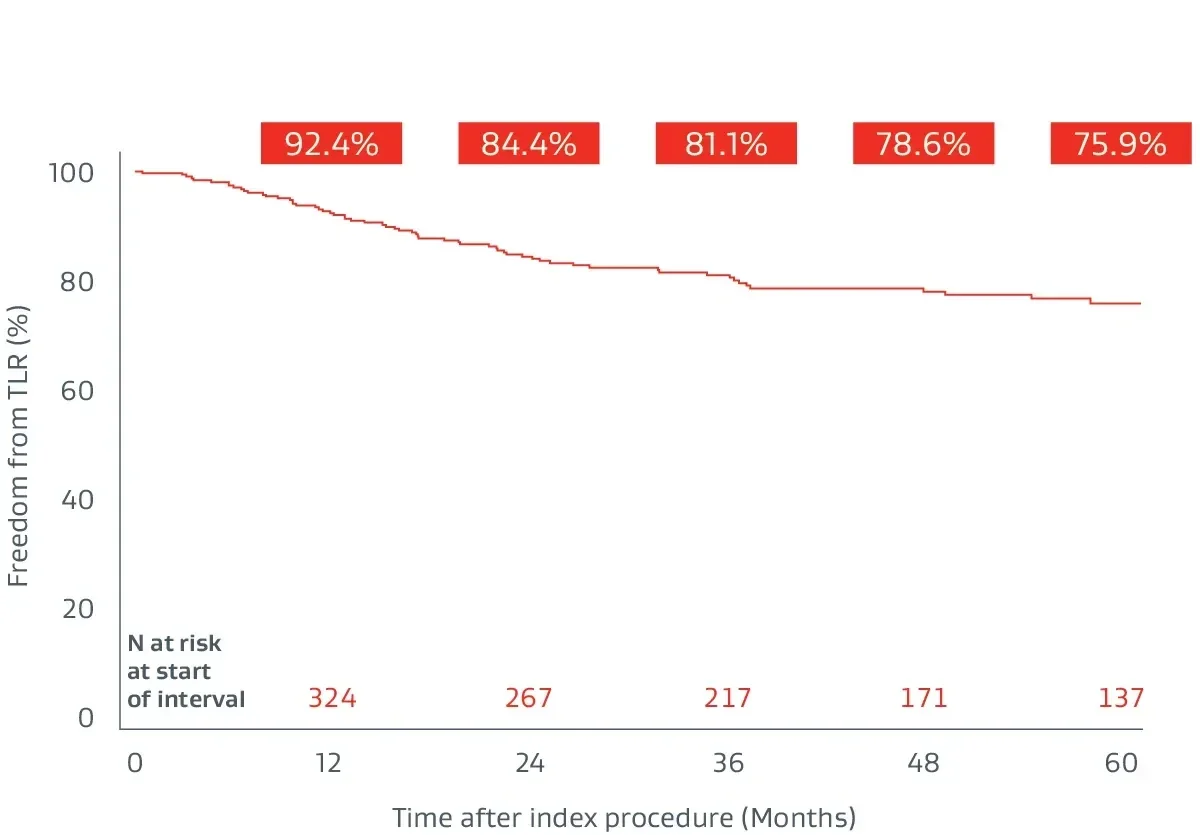
5-year freedom from target lesion revascularization (fTLR)7
Hear from physicians
Go beyond the data with key facts and findings from the physicians' perspective.
Explore practical takeaways for treating complex, long SFA disease.
Watch real results
Six-year follow-up imaging shows freedom from reocclusion despite significant popliteal lesion progression caused by chronic atherosclerotic disease.
Initial angiograms
Prior to treatment with the VIABAHN® Device
Proximal SFA
Distal SFA
Six-year follow-up angiograms
Patency maintained with the VIABAHN® Device
Proximal SFA
Distal SFA
Images courtesy of Osamu Iida, MD. Used with permission.

Peer-Reviewed Results
Access the published study outcomes in Vascular Medicine, the official journal of the Society for Vascular Medicine.
INSIGHT individual patient-level meta-analysis: 24.2-cm-long lesions and 86% of patients with advanced Rutherford classification (TASC II C/D)8
- n = 977 patients
- 70% of limbs studied (n = 1,023 limbs) were CTOs
- 24% of patients presented with CLTI
secondary patency at 1 year8
secondary patency at 5 years8
Freedom from target lesion revascularization at 1 year8
Freedom from target lesion revascularization at 5 years8
- Primary patency at 1 year was 81%8
- No difference in primary patency based on Rutherford classification, number of runoff vessels, lesion length, TASC II classification, and degree of calcification8
- Risk predictors of patency were younger age, female sex, and occlusive lesions8
- >70% of patients were asymptomatic (Rutherford classification stage 0) through 5 years8
The VIABAHN® Device demonstrated a good safety profile and acceptable patency through 5-year follow-up.8
Consider the demands of treating long-length lesions of the SFA
- Lesion length is a predictor of patency outcomes for several treatment modalities.
- Drug-eluting stents
- Lesion length has been shown to be an independent predictor of restenosis.1-4
- In a randomized study, COOK® ZILVER® PTX® Drug-Eluting Peripheral Stent has been shown to have lower patency in long lesions > 10 cm compared to those 10 cm or shorter.2
- Lesion length has been shown to be an independent predictor of restenosis.1-4
- Drug-coated balloons
- Multivariate analysis of the Medtronic IN.PACT Global Study demonstrated that increasing lesion length was a predictor of increased risk for clinically driven target lesion revascularization.3
- Multivariate analysis of the Medtronic IN.PACT Global Study demonstrated that increasing lesion length was a predictor of increased risk for clinically driven target lesion revascularization.3
- Bare metal stents
- The VIASTAR Trial demonstrated bare metal stents had lower patency when treating lesions > 20 cm than when treating lesions shorter than 20 cm.4
- The VIASTAR Trial demonstrated bare metal stents had lower patency when treating lesions > 20 cm than when treating lesions shorter than 20 cm.4
- Drug-eluting stents
- Complications increase with lesion length
- Risk of dissection after balloon angioplasty increases with lesion length ≥15 cm.9
- For many bare metal stents, the risk of stent fracture increases with lesion length and is associated with a loss of patency.10,11
- Risk of dissection after balloon angioplasty increases with lesion length ≥15 cm.9


- As used by Gore, Heparin Bioactive Surface refers to Gore’s proprietary CBAS® Heparin Surface.
- Also referred to as the GORE® VIABAHN® Endoprosthesis with PROPATEN Bioactive Surface in some regions.
- Iida O, Takahara M, Soga Y, et al; ZEPHYR Investigators. 1-year results of the ZEPHYR registry (ZILVER PTX for the femoral artery and proximal popliteal artery): predictors of restenosis. JACC Cardiovasc Interv. 2015;8(8):1105-1112. doi:10.1016/j.jcin.2015.03.022
- Bausback Y, Wittig T, Schmidt A, et al. Drug-eluting stent versus drug-coated balloon revascularization in patients with femoropopliteal arterial disease. J Am Coll Cardiol. 2019;73(6):667-679. doi:10.1016/j.jacc.2018.11.039
- Micari A, Brodmann M, Keirse K, et al; IN.PACT Global Study Investigators. Drug-coated balloon treatment of femoropopliteal lesions for patients with intermittent claudication and ischemic rest pain: 2-year results from the IN.PACT global study. JACC Cardiovasc Interv. 2018;11(10):945-953. doi:10.1016/j.jcin.2018.02.019
- Lammer J, Zeller T, Hausegger KA, et al. Heparin-bonded covered stents versus bare-metal stents for complex femoropopliteal artery lesions: the randomized VIASTAR trial (VIABAHN Endoprosthesis with PROPATEN Bioactive Surface [VIA] versus bare nitinol stent in the treatment of long lesions in superficial femoral artery occlusive disease). J Am Coll Cardiol. 2013;62(15):1320-1327. doi:10.1016/j.jacc.2013.05.079
- Saxon RR, Chervu A, Jones PA, et al. Heparin-bonded, expanded polytetrafluoroethylene-lined stent graft in the treatment of femoropopliteal artery disease: 1-year results of the VIPER (VIABAHN Endoprosthesis with Heparin Bioactive Surface in the treatment of superficial femoral artery obstructive disease) trial. J Vasc Interv Radiol. 2013;24(2):165-173. doi:10.1016/j.jvir.2012.10.004
- Iida O, Ohki T, Soga Y, et al. Twelve-month outcomes from the Japanese post-market surveillance study of the VIABAHN Endoprosthesis as treatment for symptomatic peripheral arterial disease in the superficial femoral arteries. J Endovasc Ther. 2022;29(6):855-865. doi:10.1177/15266028211067739
- Iida O, Ohki T, Soga Y, et al. Five-year outcomes of the GORE VIABAHN Endoprosthesis for the treatment of complex femoropopliteal lesions from a Japanese postmarket surveillance study. Vasc Med. 2024;29(4):416-423. doi:10.1177/1358863X241233528
- Reijnen MMJP. Outcomes of the VIABAHN Endografts (Gore) to treat fem-pop occlusive disease; data from the INSIGHT individual patient data meta-analysis. Presented at: Vascular Endovascular Issues Techniques Horizons (VEITHsymposium); November 18-22, 2025; New York, NY. Presentation 730.
- Hong H, Park UJ, Roh YN, Kim HT. Predictive factors of severe dissection after balloon angioplasty for femoropopliteal artery disease. Ann Vasc Surg. 2021;77:109-115. doi:10.1016/j.avsg.2021.05.048
- Iida O, Nanto S, Uematsu M, Ikeoka K, Okamoto S, Nagata S. Influence of stent fracture on the long-term patency in the femoro-popliteal artery: experience of 4 years. JACC Cardiovasc Interv. 2009;2(7):665-671. doi:10.1016/j.jcin.2009.04.014
- Scheinert D, Scheinert S, Sax J, et al. Prevalence and clinical impact of stent fractures after femoropopliteal stenting. J Am Coll Cardiol. 2005;45(2):312-315. doi:10.1016/j.jacc.2004.11.026

Refer to Instructions for Use at eifu.goremedical.com for a complete description of all applicable indications, warnings, precautions and contraindications for the markets where this product is available. RXOnly
INDICATIONS FOR USE IN THE US: The GORE® VIABAHN® Endoprosthesis with Heparin Bioactive Surface is indicated for improving blood flow in patients with symptomatic peripheral arterial disease in superficial femoral artery de novo and restenotic lesions up to 270 mm in length with reference vessel diameters ranging from 4.0 – 7.5 mm. The GORE® VIABAHN® Endoprosthesis with Heparin Bioactive Surface is indicated for improving blood flow in patients with symptomatic peripheral arterial disease in superficial femoral artery in-stent restenotic lesions up to 270 mm in length with reference vessel diameters ranging from 4.0 – 6.5 mm. The GORE® VIABAHN® Endoprosthesis with Heparin Bioactive Surface is indicated for improving blood flow in patients with symptomatic peripheral arterial disease in iliac artery lesions up to 80 mm in length with reference vessel diameters ranging from 4.0 – 12 mm. The GORE® VIABAHN® Endoprosthesis with Heparin Bioactive Surface is also indicated for the treatment of stenosis or thrombotic occlusion at the venous anastomosis of synthetic arteriovenous (AV) access grafts.
CONTRAINDICATIONS: The GORE® VIABAHN® Endoprosthesis with Heparin Bioactive Surface is contraindicated for non-compliant lesions where full expansion of an angioplasty balloon catheter was not achieved during pre-dilatation, or where lesions cannot be dilated sufficiently to allow passage of the delivery system. Do not use the GORE® VIABAHN® Endoprosthesis with Heparin Bioactive Surface in patients with known hypersensitivity to heparin, including those patients who have had a previous incident of Heparin-Induced Thrombocytopenia (HIT) type II.